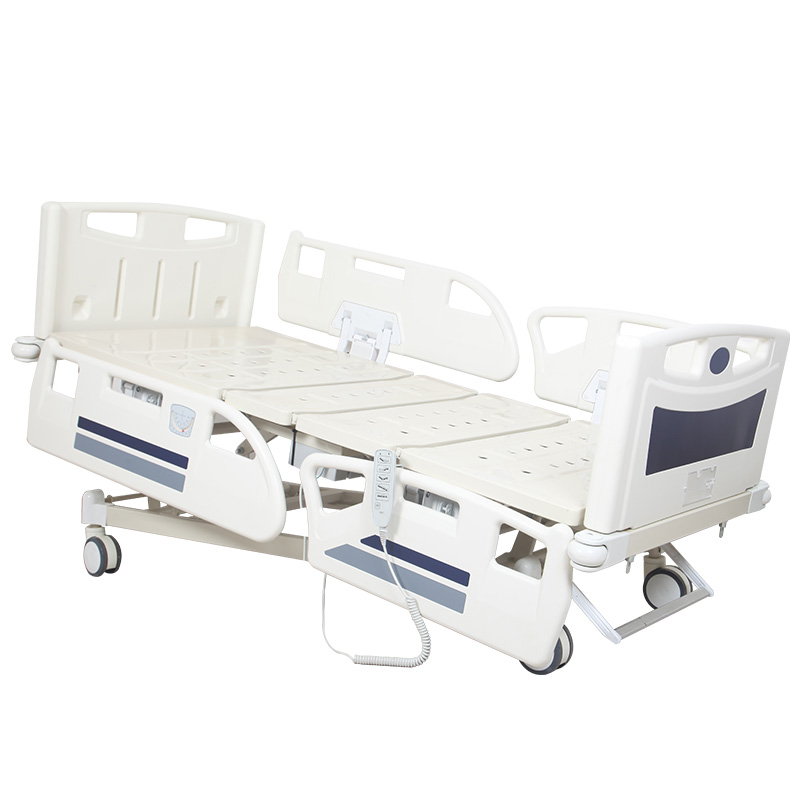
A patient is positioned comfortably in an electric hospital bed. The caregiver raises the backrest for eating, conversation, examination, or daily care. A short time later, the patient has moved noticeably toward the foot end of the bed. The caregiver pulls the patient back up. Then the same thing happens again. This is a common and frustrating positioning problem. Many users immediately suspect that the mattress is too slippery, but mattress friction is only one possible cause. Sliding can also be influenced by backrest angle, knee-section position, the patient's starting position, clothing and bedding, mattress construction, body shape, mobility level, and the way the electric bed moves during articulation. Before replacing the mattress or assuming that the bed is defective, caregivers and equipment buyers should examine the complete positioning system. A properly configured Electric Hospital Bed should allow caregivers to use backrest and leg adjustments in a coordinated way according to the patient's care requirements rather than treating each motor as an independent feature. Not every positioning problem is the same. If sliding begins immediately as the backrest moves, bed geometry and patient starting position deserve attention. If the patient remains stable initially but gradually moves over time, mattress surface, bedding, body movement, and sustained sitting position may also contribute. Electric hospital beds make it easy to raise the upper body with the push of a button. That convenience can also lead to one common mistake: raising the backrest higher than necessary and leaving the patient in that position for an extended period. The ideal position for eating may not be the same as the position for resting. Caregivers should use bed positioning according to the patient's clinical and care requirements rather than automatically raising the backrest to its maximum angle. One of the most useful features of a multi-function electric hospital bed is the ability to adjust more than the backrest. If the upper body is raised while the lower platform remains completely flat, the patient may have less positional support against downward movement. Electric beds may allow caregivers to: Their combined movement influences the shape of the complete sleeping surface. Positioning should always follow the individual patient's clinical requirements and professional care guidance. Some electric hospital beds provide coordinated backrest and knee-section movement, often described as auto-contour or a similar combined positioning function. Instead of raising only the upper-body section while leaving the lower body completely flat, the bed coordinates multiple sections to create a more supportive sitting profile. Manufacturers may use different terms for similar positioning functions. Buyers should not assume that every “auto-contour” system uses exactly the same angles, timing, or mechanical sequence. The starting position matters before the bed moves. If the patient's pelvis is already positioned significantly below the intended backrest pivot area, raising the backrest may exaggerate downward movement. Where repositioning is required, caregivers should use appropriate patient-handling techniques and assistance according to facility procedures. Sometimes the first suspicion is correct. The interaction between the patient, clothing, sheets, and mattress cover can affect how easily the body moves across the surface. Do not evaluate only the bare mattress cover. The real contact system can include: A mattress that appears acceptable by itself may behave differently when combined with smooth bedding and patient clothing. An adjustable bed mattress needs to bend with the articulated platform. A mattress that resists bending can behave differently as the backrest rises. The mattress should be compatible with the bed's intended articulation range. Sometimes the patient is not sliding independently. The entire mattress is gradually moving toward the footboard. Check: For equipment evaluation, buyers can temporarily note the mattress position relative to the platform and operate several complete adjustment cycles. If the mattress itself moves, the problem is different from the patient's body sliding over a stable mattress. Two patients on the same bed may respond differently to exactly the same position. Hospital bed positioning needs to reflect the individual user's condition and care plan. If caregivers need to move the same patient toward the head of the bed repeatedly during every shift, the problem should not simply become part of the normal routine. The bed position, mattress, bedding, patient mobility, and care method should be reviewed together. Procurement specifications often focus on maximum backrest angle. For example, buyers may compare whether a bed can reach 70°, 75°, or another maximum value. The actual experience depends on: Buyers should evaluate how the complete bed feels and behaves throughout the movement range. An electric actuator creates movement through the bed's mechanical linkage. Where the platform bends relative to the patient's body can influence how much relative movement occurs between the patient and mattress. The mechanism and geometry behind the published angle matter. Some higher-specification hospital beds use designs intended to create additional space as the backrest rises. Manufacturers may describe this as auto-regression, backrest regression, or similar terminology. Depending on the specific design, this may influence: Ask the manufacturer to demonstrate the actual mechanical movement. This is much more useful than checking only whether the motors operate. Use the mattress intended for the final order and position an appropriate test load or conduct evaluation according to the manufacturer's test procedure. Observe how the mattress and complete system behave during each step. A bare hospital bed platform tells you very little about real patient positioning. The mattress used during testing should match the mattress planned for mass production whenever possible. This should not be treated as a general-purpose solution. Trendelenburg positioning is a clinical bed function and should be used only when appropriate for the patient's clinical care and according to professional procedures. If the problem is caused by excessive backrest elevation, poor mattress fit, or incorrect initial patient position, those causes should be corrected directly. No. Knee adjustment can influence the shape of the bed surface, but it is not a universal solution for every user. Equipment flexibility is valuable because different patients require different configurations. This is a useful clue. After the activity is complete, the bed can be returned to the position specified in the patient's care plan. If significant movement occurs even when the backrest is relatively low, the problem may require a different assessment. The timing and circumstances need to be observed. A mattress selected for pressure redistribution may have different surface and construction characteristics from a standard foam mattress. Pressure-management requirements should be addressed according to appropriate clinical assessment while maintaining compatibility with the hospital bed. Patient sliding may initially appear to be only a nursing issue. But repeated complaints across many beds can also indicate a procurement problem. If the equipment makes a routine position unnecessarily difficult to maintain, product configuration deserves evaluation. A distributor may successfully deliver an electric hospital bed that passes all basic function tests but later receive complaints that patients continually slide toward the foot end. Good product training can prevent some problems from being incorrectly diagnosed as mechanical defects. Some buyers prefer independent control because it provides flexibility for different patient positions. Depending on the bed model, options may include: Procurement teams should understand how nurses will actually use them. Bed positioning depends partly on control design. A technically advanced bed is less useful if caregivers cannot quickly select the required movement. Some higher-specification electric and ICU beds provide staff controls at the footboard. Do not evaluate only the number of buttons. Check whether routine positions can be reached quickly and logically. A five-function bed is not automatically better at patient positioning than every three-function bed simply because it has more motors. A useful specification explains the care problem behind the movement rather than simply listing five electrical functions. Pulling a patient toward the head of the bed may temporarily restore position, but it does not explain why the movement keeps happening. The more useful approach is to identify whether the problem starts with excessive backrest elevation, an unsupported lower-body position, poor starting position, mattress movement, low-friction surfaces, or limitations in the patient's ability to maintain posture. Electric hospital beds provide valuable positioning flexibility because caregivers can change several parts of the sleeping platform independently or in combination. But that flexibility works best when the bed, mattress, controls, and positioning method are treated as one complete system. For procurement teams, this is also why evaluating an electric hospital bed should go beyond checking whether every motor moves. The real test is whether those movements create practical, stable positions for everyday patient care. During sample evaluation, do not simply press every button once. Install the final mattress, create a realistic sitting position, and observe what happens through repeated backrest and knee-section adjustments. If the mattress shifts or the test setup consistently moves toward the foot end, investigate the bed geometry and mattress combination before approving mass production. If you are sourcing electric hospital beds for hospitals, distributors, healthcare projects, or OEM programs, Contact Us to discuss backrest geometry, auto-contour functions, mattress compatibility, control systems, and suitable electric bed configurations.If the Patient Slides Down Every Time the Backrest Goes Up, the Mattress May Not Be the Real Problem
First Confirm What “Sliding Down” Actually Looks Like
Observe Whether the Patient:
The Timing of the Movement Provides an Important Clue
1. The Backrest May Be Raised Too High for Too Long
As the Backrest Angle Increases:
Use the Angle Required for the Activity
2. The Knee Section May Be Completely Flat
Depending on the Patient and Care Plan, Knee or Leg Adjustment May Help Create a More Supported Position
Do Not Think of the Back and Leg Motors as Unrelated Functions
3. Check Whether the Bed Has an Auto-Contour Function
The Basic Idea Is Simple
Ask Exactly What the Function Does
4. The Patient May Be Starting Too Far Down the Mattress
Before Adjusting the Bed, Check:
Do Not Use the Motor to Correct an Already Poor Starting Position
5. The Mattress Surface May Be Too Slippery
Check the Complete Surface Combination
Several Low-Friction Layers Can Combine
6. The Mattress May Be Too Rigid to Follow the Bed Platform
Possible Signs Include:
A Household Mattress Is Not Automatically Suitable for an Electric Hospital Bed
7. Check Whether the Mattress Itself Is Moving
Watch the Mattress Edges While the Bed Moves
Mark the Starting Position During a Test
8. Patient Body Shape and Mobility Can Change the Result
Differences Can Include:
There Is No Universal Bed Angle That Works for Every Patient
9. Repeatedly Pulling the Patient Back Up Is a Sign to Reassess the Setup
Repeated Repositioning Can Increase:
Look for the Cause Before Creating a Repetitive Manual Task
Backrest Angle Is Not the Same as Sitting Comfort
But a Larger Maximum Angle Does Not Automatically Produce Better Positioning
Maximum Angle Is Only One Specification
Why the Location of the Backrest Pivot Matters
During Sample Testing, Observe:
Two Beds With the Same 75° Specification Can Feel Different
What Is Auto-Regression on a Hospital Bed?
The Mechanism Changes How the Back Section Moves Relative to the Bed Frame
Do Not Compare the Marketing Term Alone
How Buyers Can Test Sliding on a Sample Electric Hospital Bed
Start With the Bed Flat
Then Operate the Bed Through Realistic Positions
Do Not Test the Bed Without the Final Mattress
The Mattress Influences:
Sample Approval Should Use the Final Configuration
Should You Use Trendelenburg to Stop a Patient Sliding Down?
Do Not Use Clinical Positioning Functions Simply as Mechanical Anti-Slide Tools
Can Raising the Knee Section Solve Every Sliding Problem?
The Patient May Have:
Use Functions According to the Care Plan
What If the Patient Slides Mainly During Meals?
Observe:
Meal Position and Resting Position Do Not Need to Be Identical
What If the Patient Slides During Sleep?
Consider:
Do Not Assume Every Downward Movement Is Caused by the Electric Motor
Sliding and Pressure Management Are Not the Same Problem
When Changing Support Surfaces, Recheck:
Do Not Solve One Problem While Creating Another
Why This Problem Matters to Hospital Procurement Teams
If Multiple Users Report the Same Issue, Review:
Do Not Automatically Blame Staff Technique
Why This Problem Also Matters to Distributors
This Creates After-Sales Questions About:
Demonstrate Positioning Before Delivery
Ask Whether Back and Leg Functions Can Be Operated Independently
Others May Also Value Preset or Combined Functions
More Functions Are Useful Only When They Improve Real Care
Check Whether the Hand Controller Makes Positioning Easy to Understand
A Good Controller Should Help Users Distinguish:
Confusing Controls Can Lead to Poor Bed Setup
Footboard Controls Can Help Staff Manage More Complex Bed Functions
These May Support:
Evaluate the Interface During Sample Approval
What Should Buyers Ask the Manufacturer About Patient Sliding?
Do Not Compare Electric Beds Only by the Number of Motors
Positioning Quality Depends on:
Ask What Each Function Solves
Common Reasons Patients Slide Down in an Electric Hospital Bed
Electric Hospital Bed Positioning Checklist
If the Patient Keeps Sliding Down, Stop Treating Repositioning as the Only Solution
Expert Tip